
Hip · Anterior & personalised replacement
Is an anterior hip replacement the best way to do it?
Short answer: it is a very good way. It is not the only way, and it is not right for every hip.
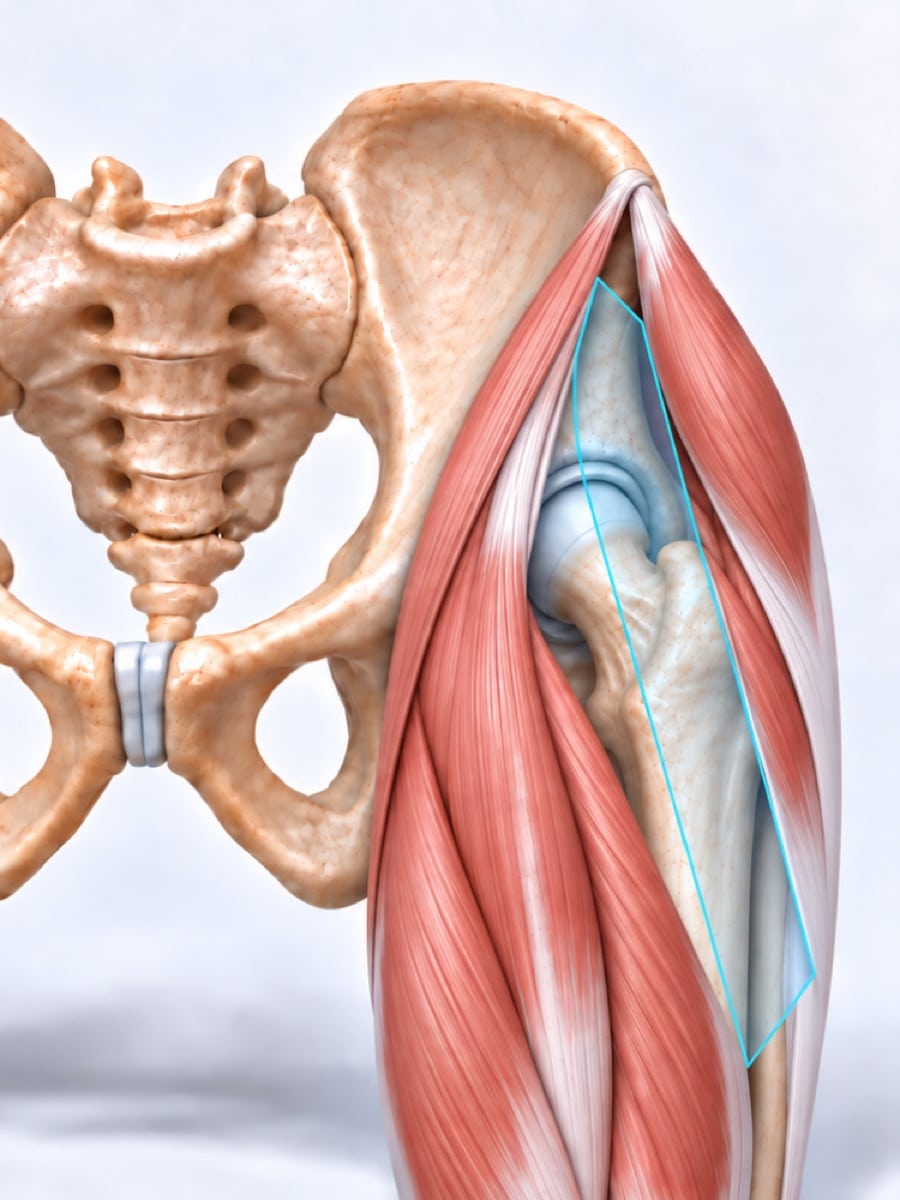
An anterior hip replacement is a hip replacement done through the front of the hip. The surgeon goes between the muscles instead of cutting through them. People tend to walk more easily in the first few weeks. By six months, studies show people feel the same whether the hip was done from the front or the back. Dr Yas Edirisinghe, specialist orthopaedic surgeon in Adelaide, does most of his hip replacements, including redo operations, through the front. He also does posterior hips, and there are situations where he recommends one. His view: it is not about what the surgeon is good at, or used to. No one approach is right for every patient, every time.

Is anterior better?
Better in the first few weeks, yes. Better after that? The studies say no.
People who have an anterior hip have less pain in the first days and walk better in the first weeks. By six months there is no difference. 1,2
Read why ↓I had a posterior hip. Is mine worse?
No.
Posterior hips are the most common hip replacement in the world. At six months and a year, people with posterior hips do just as well. 1
Read why ↓Which approach should I have?
For most people, anterior. For some, posterior.
Your body shape, where your pain is, what has been done before, and the shape of your bones all matter. Dr Yas does most of his hips from the front, and recommends the posterior approach when it will give you a better result. In his words: “No one approach is right for every patient, every time.”
Read why ↓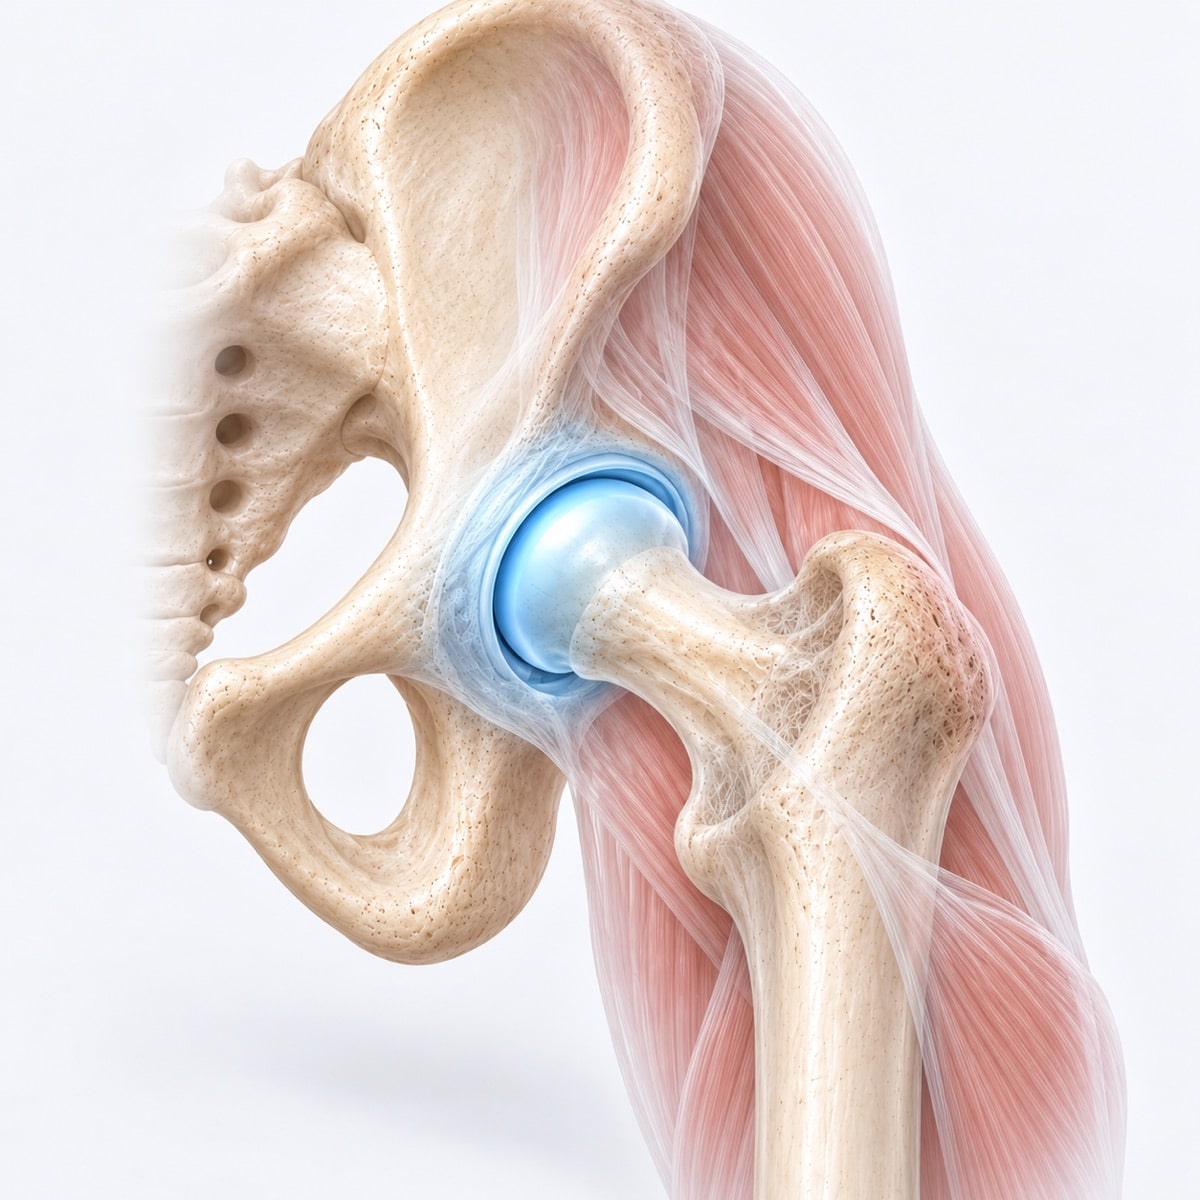
What an anterior hip replacement actually is
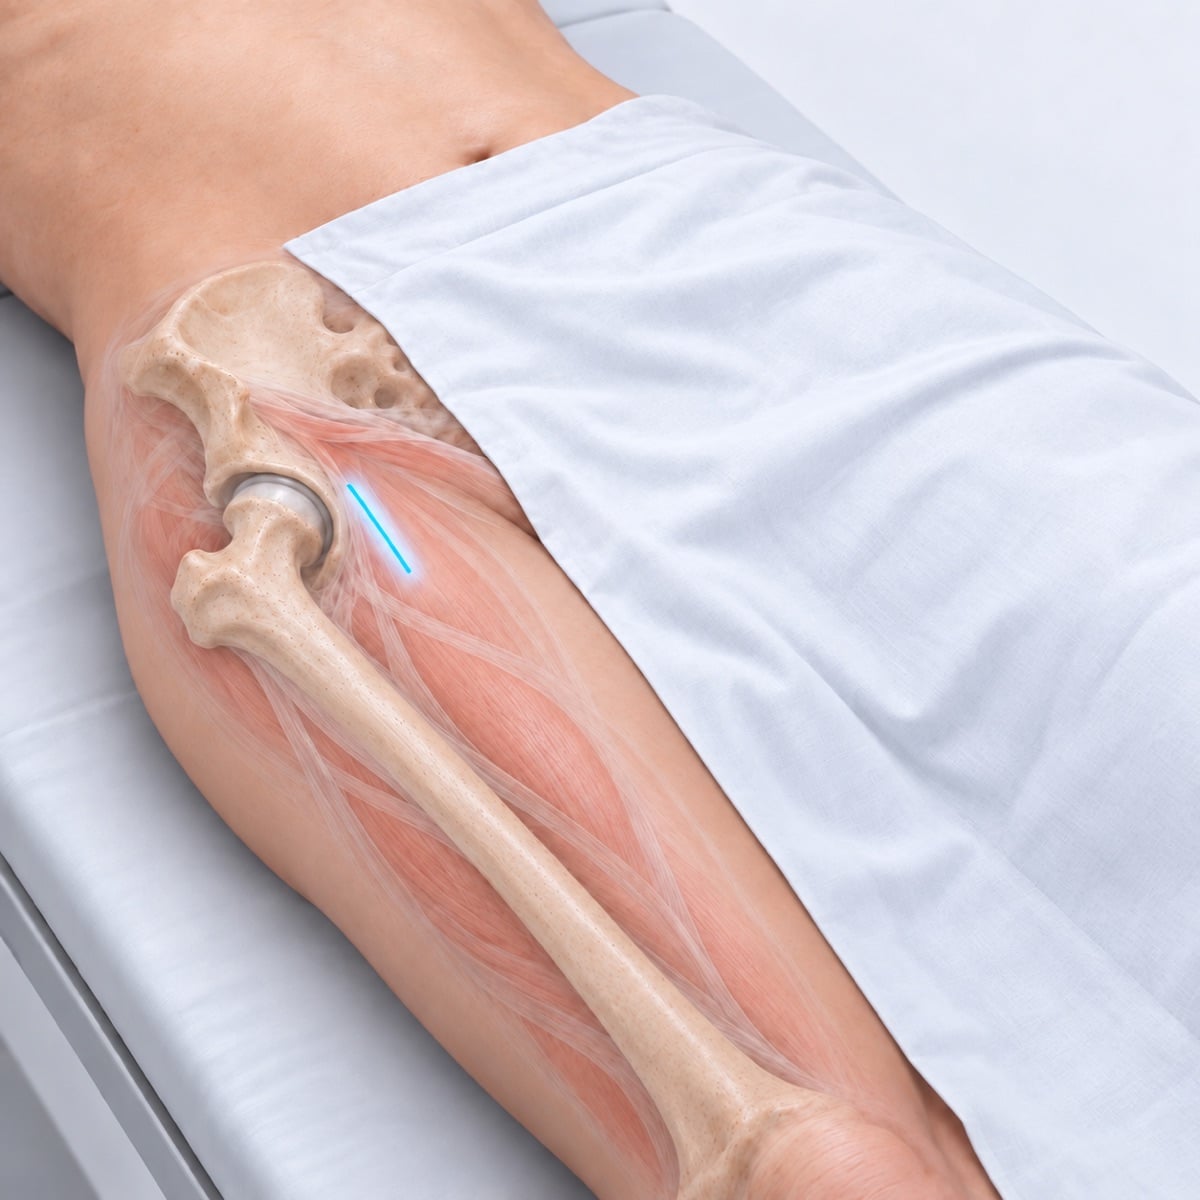
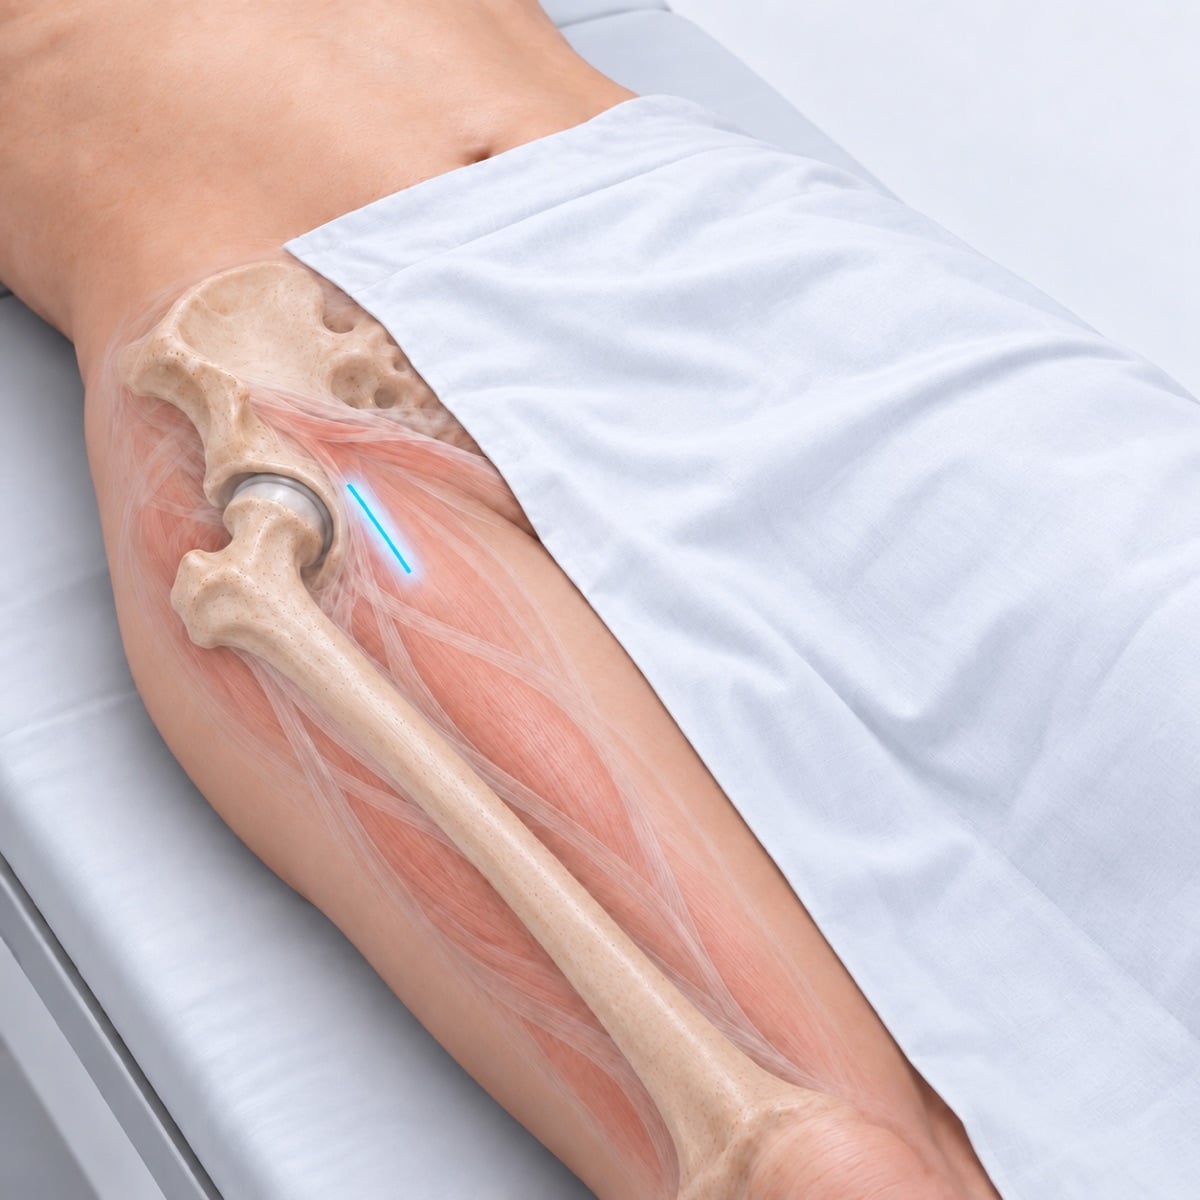
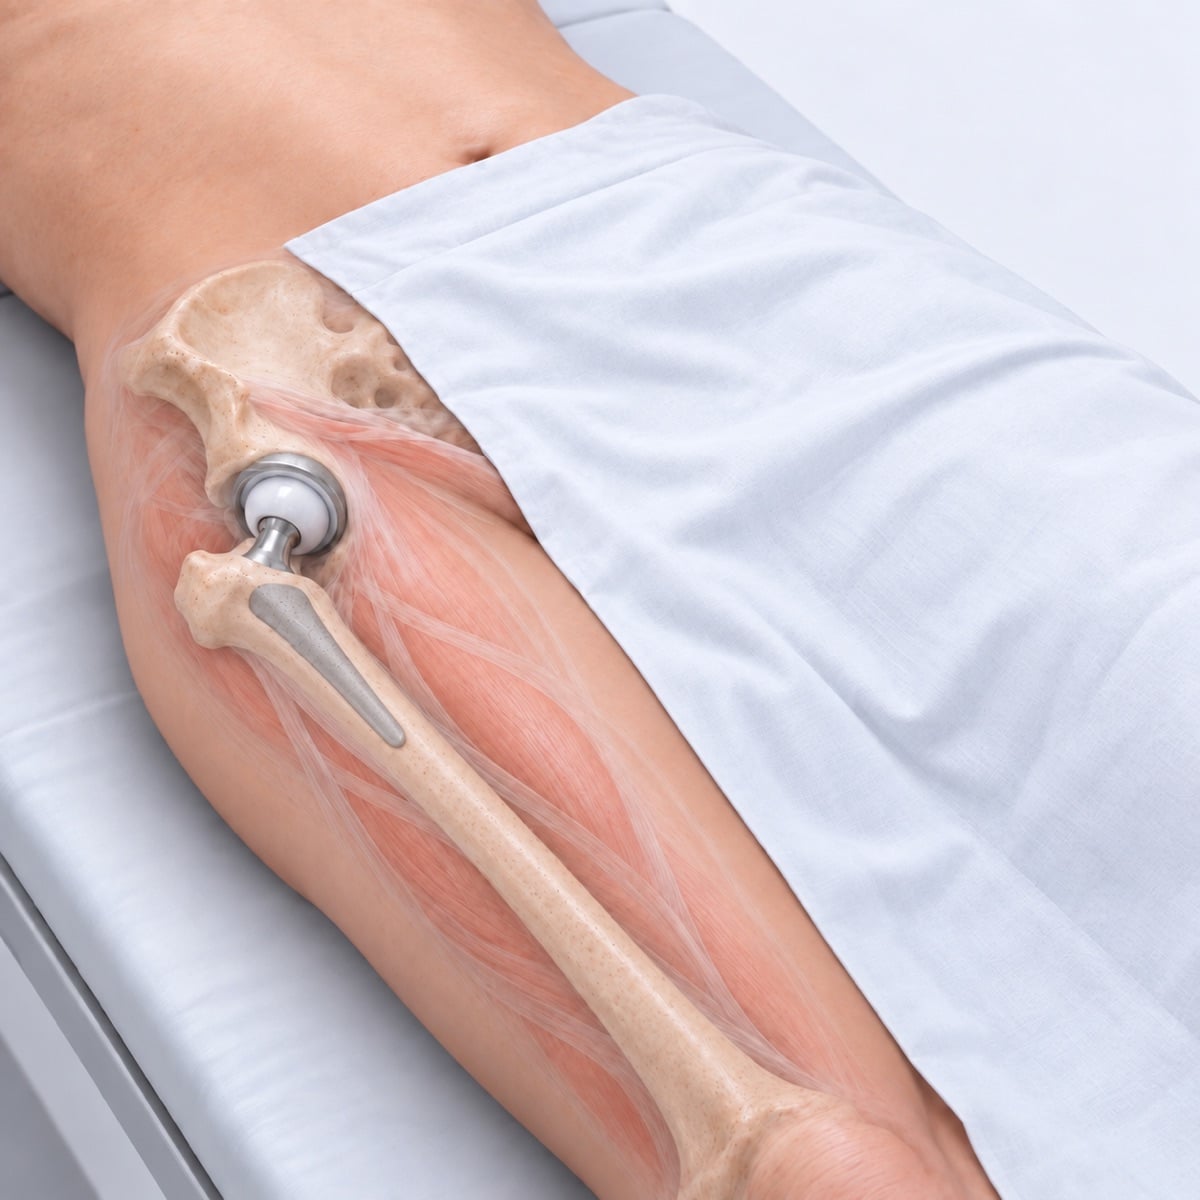
Every hip replacement does the same job. The worn ball and socket are taken out. A new socket goes into the pelvis. A new ball on a stem goes into the thigh bone. What changes is the way in.
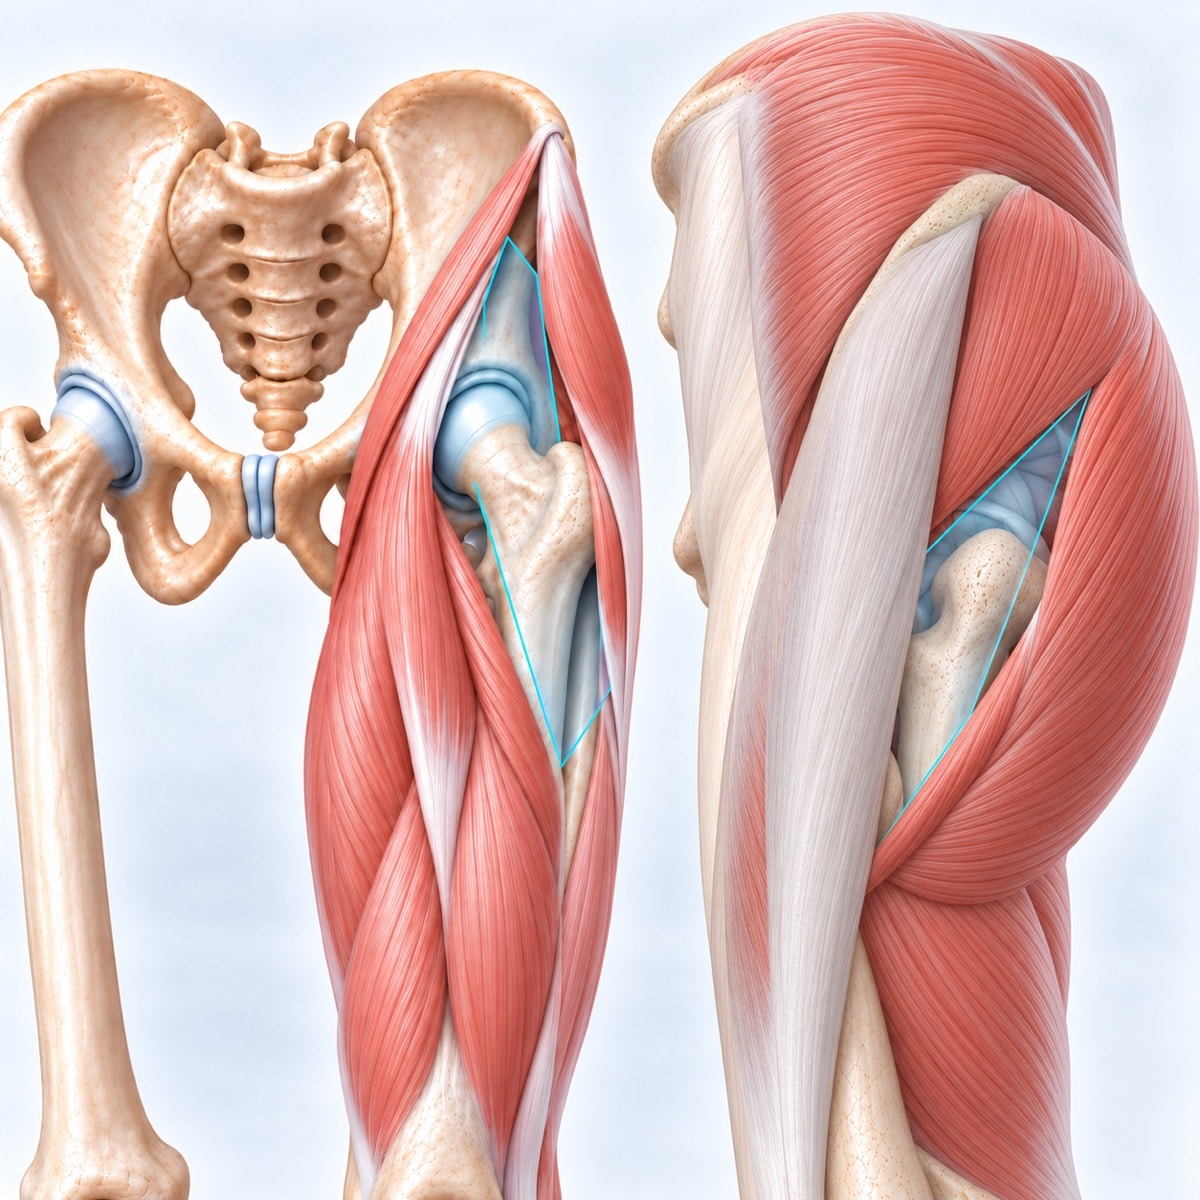
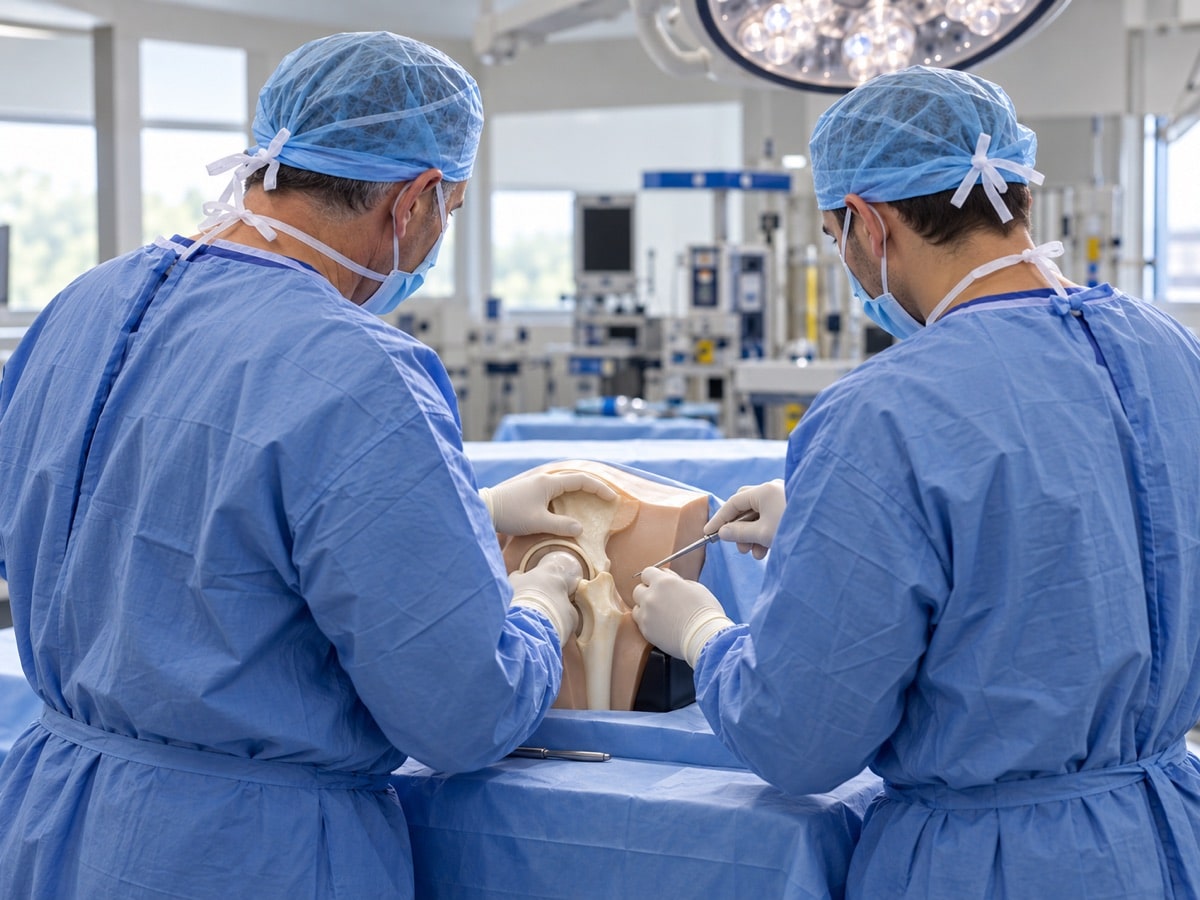
Anterior means from the front. You lie on your back. The cut is at the front of the hip, near the crease of the groin. The surgeon goes through a natural gap between two muscles. No muscle is cut off the bone. That is why it is called “muscle-sparing”.
Posterior means from the back. You lie on your side. The cut is at the back of the hip, over the buttock. The surgeon splits the big buttock muscle along its fibres and lifts a few small muscles off the bone to get in. They are stitched back at the end.
Lateral means from the side. The cut is over the side of the hip. Part of the muscle that holds your pelvis level is lifted off the bone. Dr Yas does not use this approach, and the reason is below.
Once the surgeon is inside, the operation is the same. Same implants. Same job. Same lifetime.
What "anterior" does, and doesn't, mean
| Anterior means | Anterior does not mean |
|---|---|
| The cut is at the front, and no muscle is cut off the bone | A different kind of hip replacement, or a different implant |
| Less pain in the first few days, and better walking in the first weeks 1,2 | A better hip at six months or a year 1 |
| Fewer redo operations for the hip popping out (dislocation) in the Australian registry 4 | No risk. It has its own risks, explained below |
| The surgeon can X-ray the hip during surgery to check the position | The scar is always smaller, or the recovery is always faster |
First, where does your hip pain come from?
This matters more than you would think, and it decides the approach.
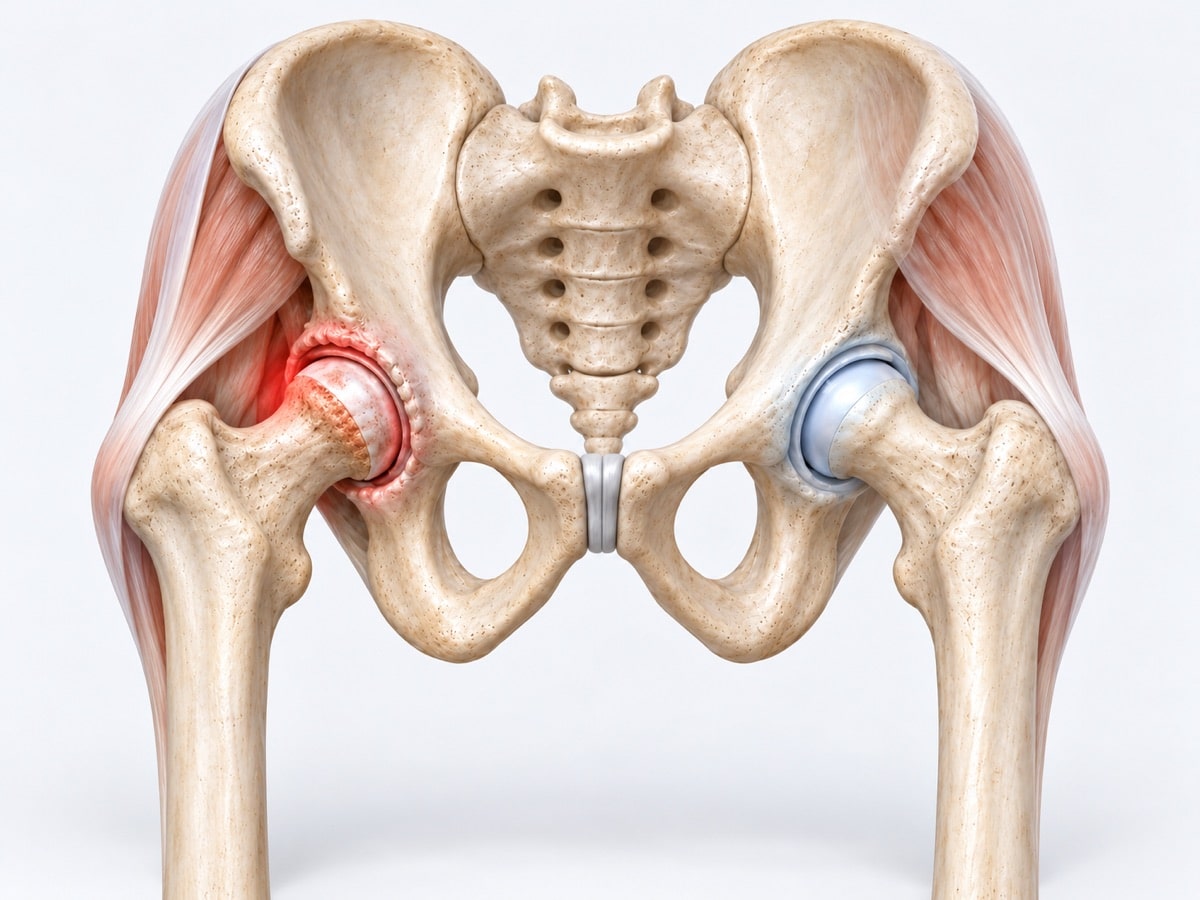

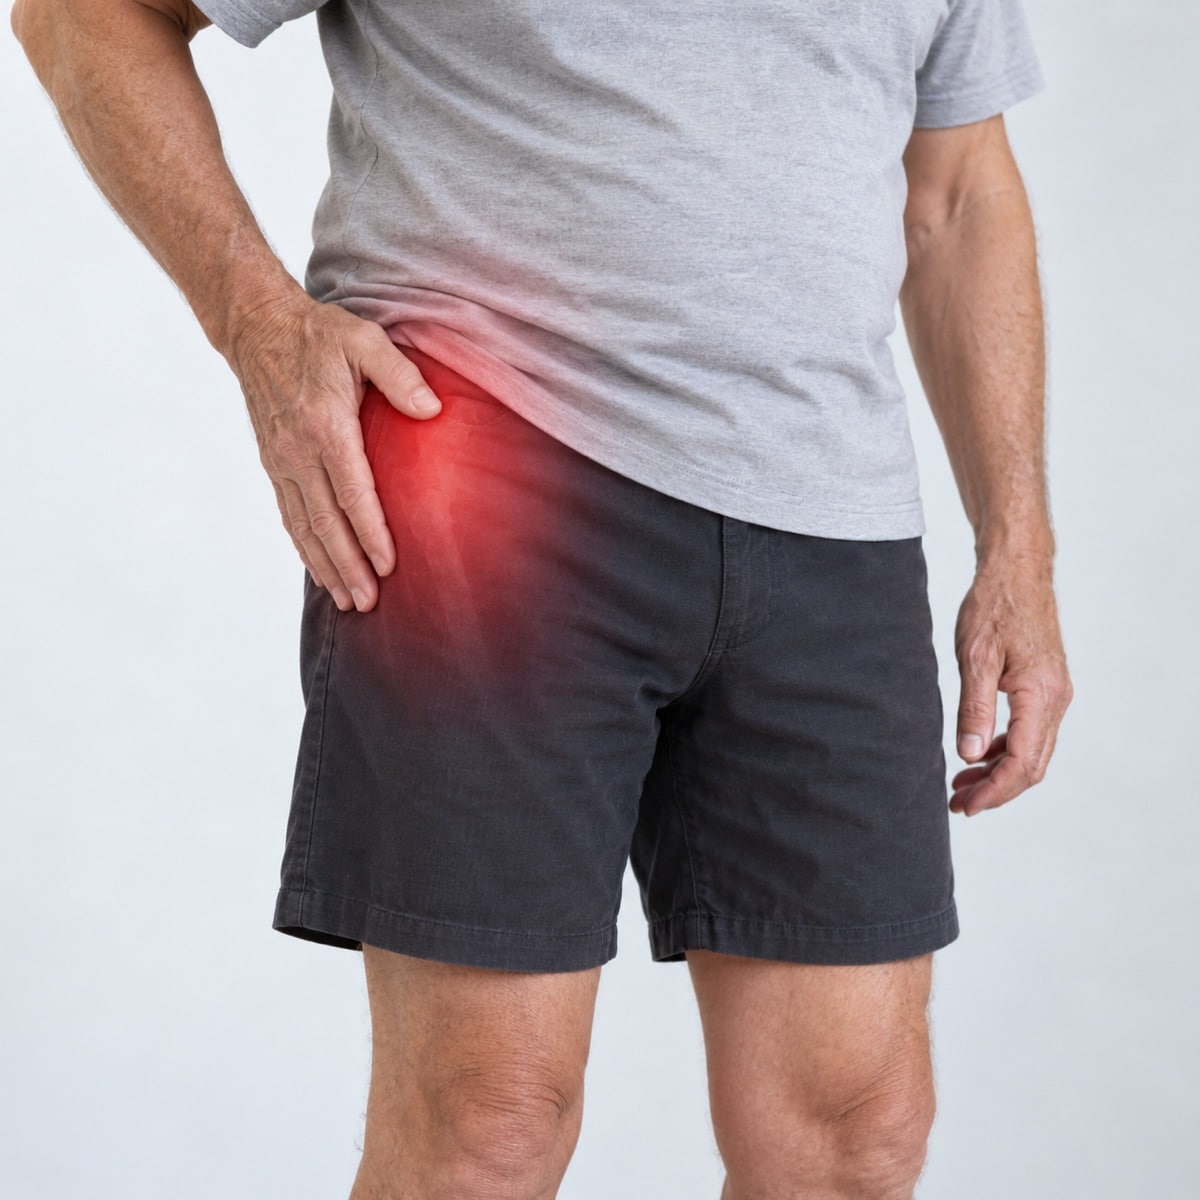
Groin pain and stiffness is the joint. Hip arthritis hurts in the groin and makes the hip stiff. Putting on socks and shoes gets hard. Getting out of a low chair or a car takes a moment. The first steps after sitting are stiff and sore. Some people feel it down the front of the thigh, or even in the knee.
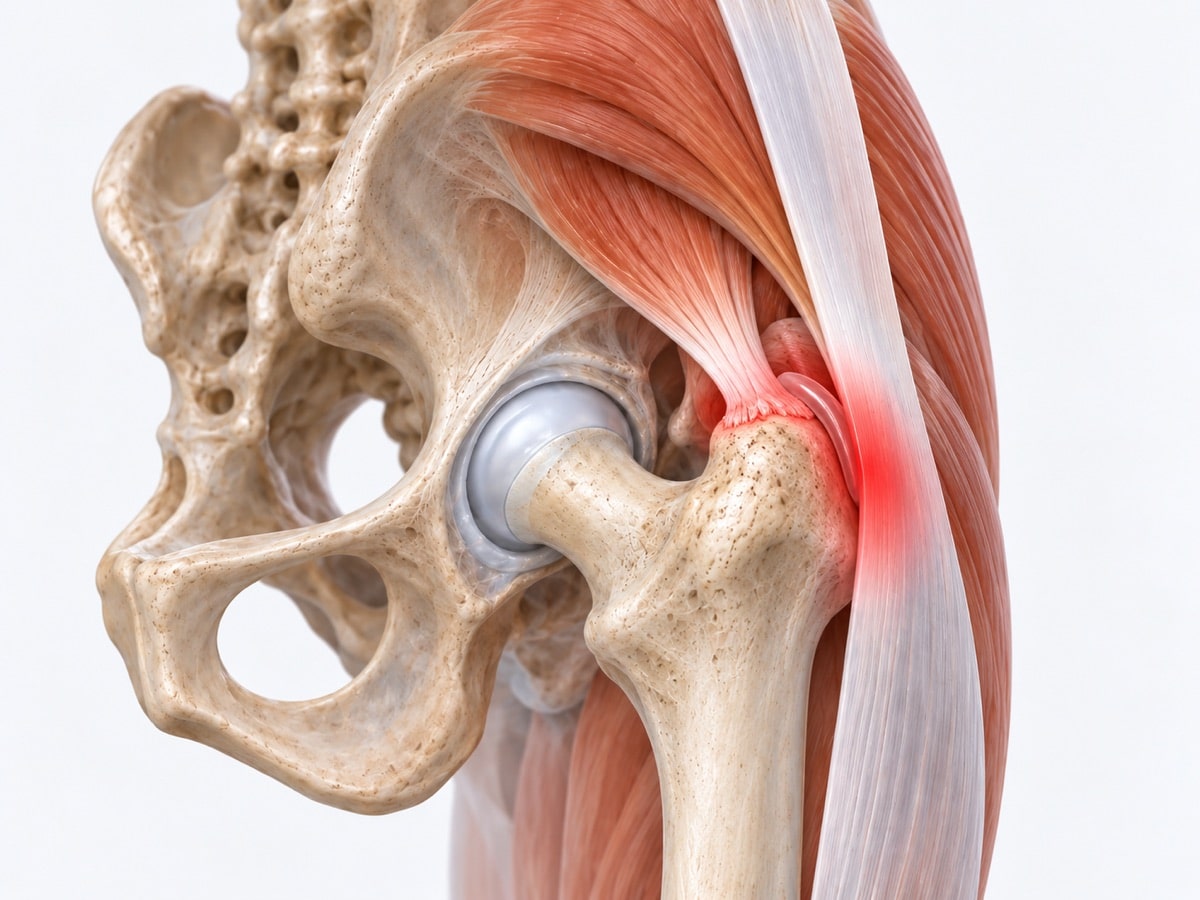

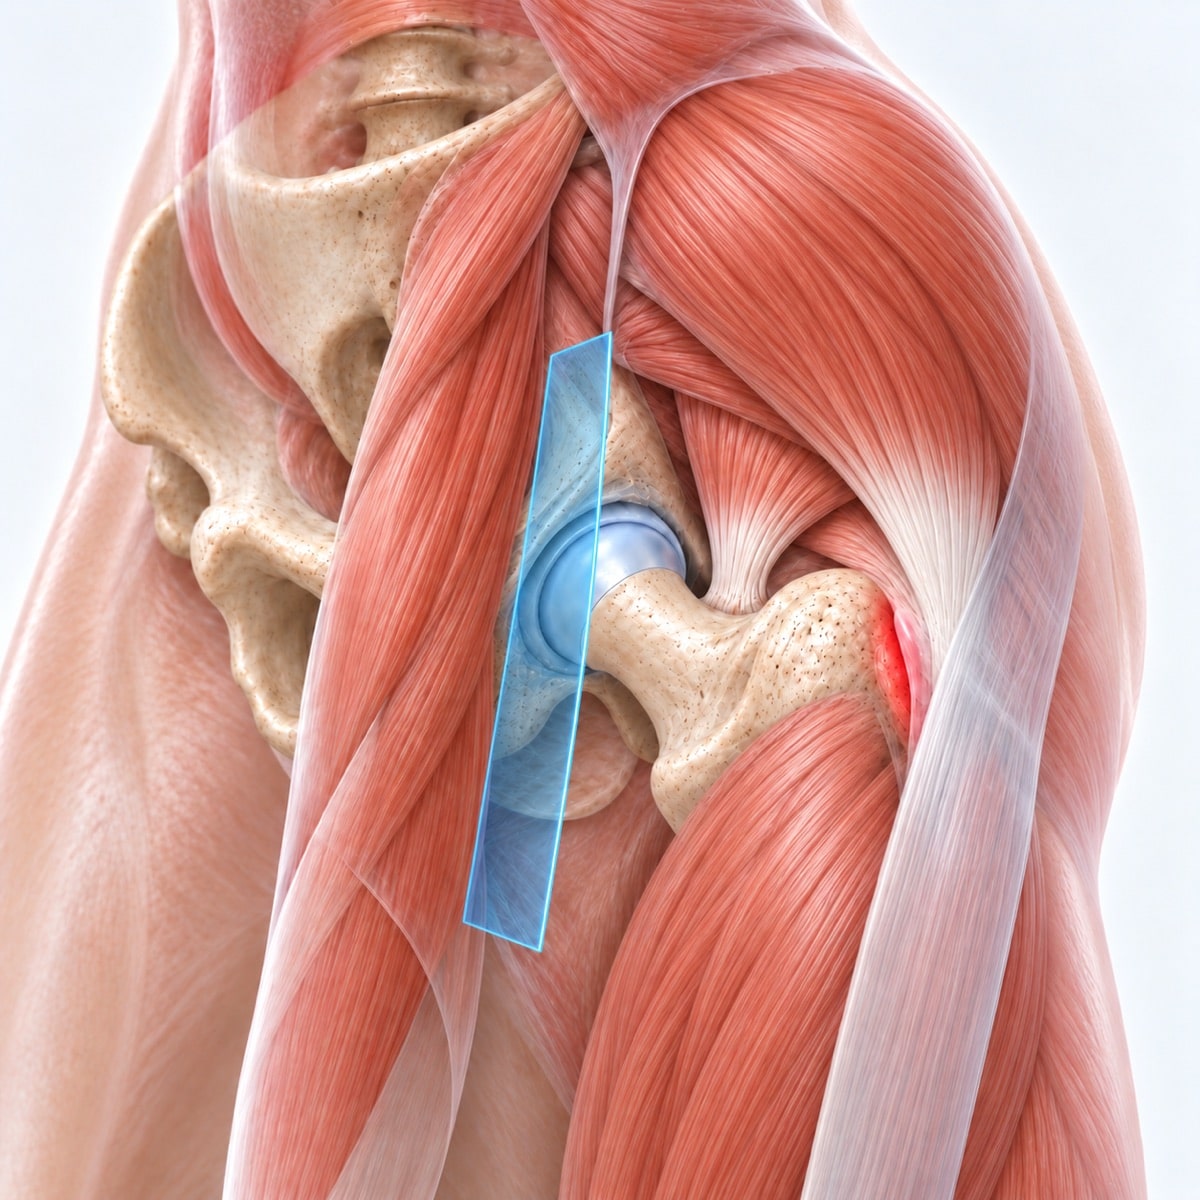
Pain on the side of the hip is the tendons and the bursa. On the bony point at the side of your hip, a long band of tendon (the iliotibial band) runs over a small fluid cushion (the bursa), and the tendons of the muscles that hold your pelvis level attach there. When the band gets tight and inflamed, or the bursa swells, it hurts to lie on that side at night, to climb stairs and to stand on one leg. Doctors call this iliotibial band tendinitis, trochanteric bursitis, or gluteal tendinopathy. In one large community study it affected about one adult in six, and most of them were women. 10
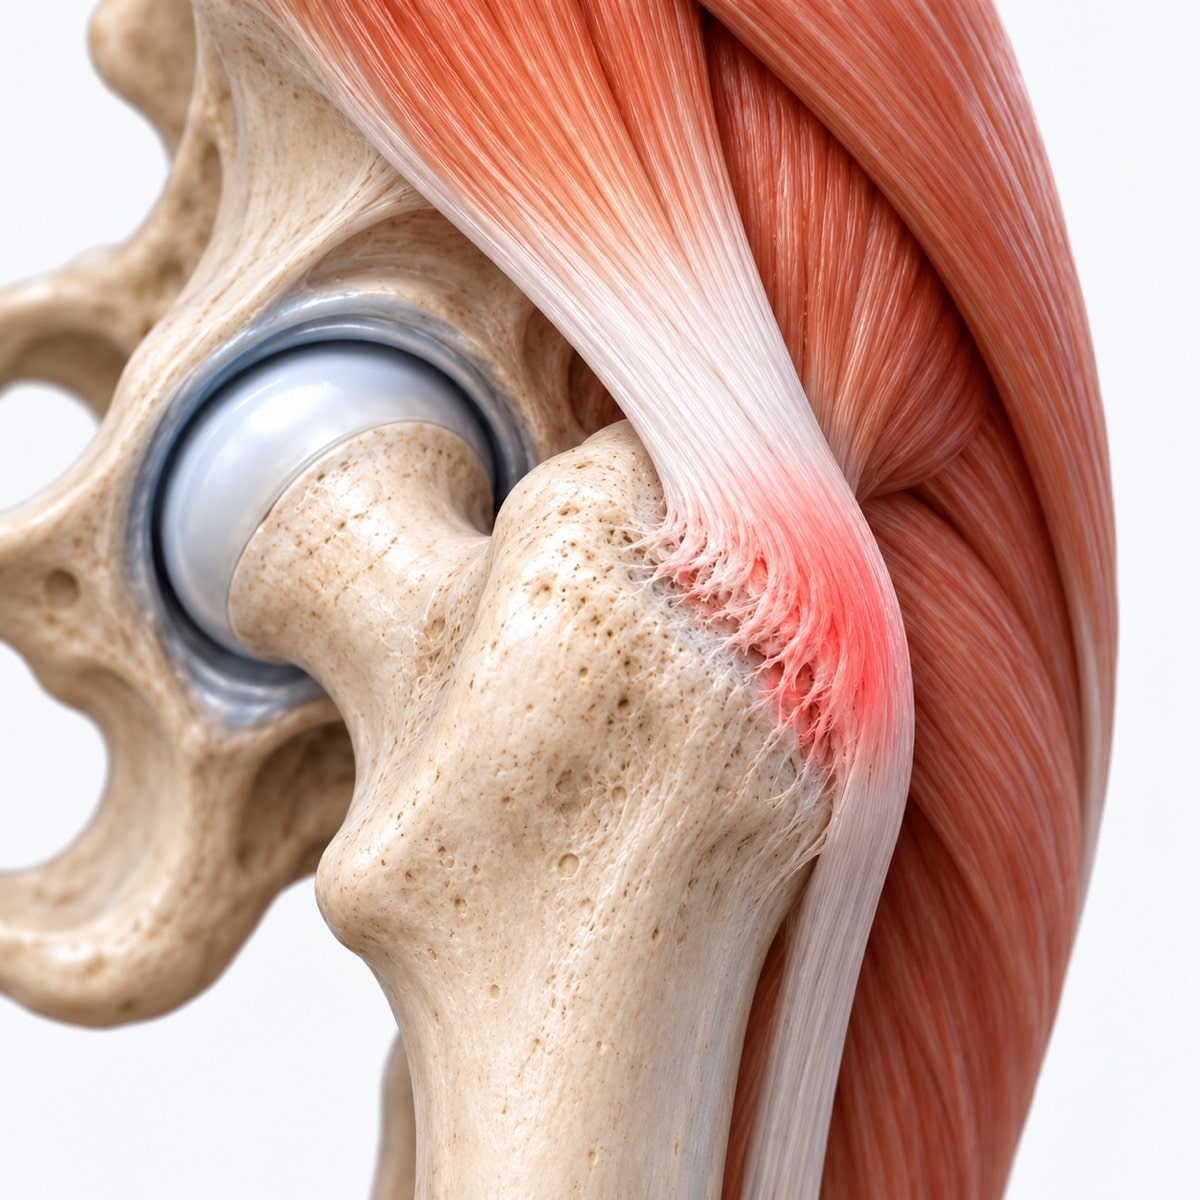
A “torn” tendon at the side is usually wear, not an injury. Many people are told they have a tear in a gluteal tendon and assume they must have fallen or ripped something. Usually they haven’t. These tendons wear thin with age, the way a rope frays, until part of it gives way. It happens slowly, with age, and it is common.

Many people have both. A worn joint changes the way you walk, and that loads the tendons and the bursa at the side. In one series of 877 hips sent to a specialist clinic for side-of-hip pain, about half had worn gluteal tendons. 10
Why it matters: an anterior hip replacement fixes the joint. It cannot reach the side of the hip. Through the back or the side, the swollen bursa can be taken out easily in the same operation, and a worn tendon can be repaired. If your pain is coming from both places, that changes the plan. Hip pain explained
Anterior, posterior and lateral: the honest comparison
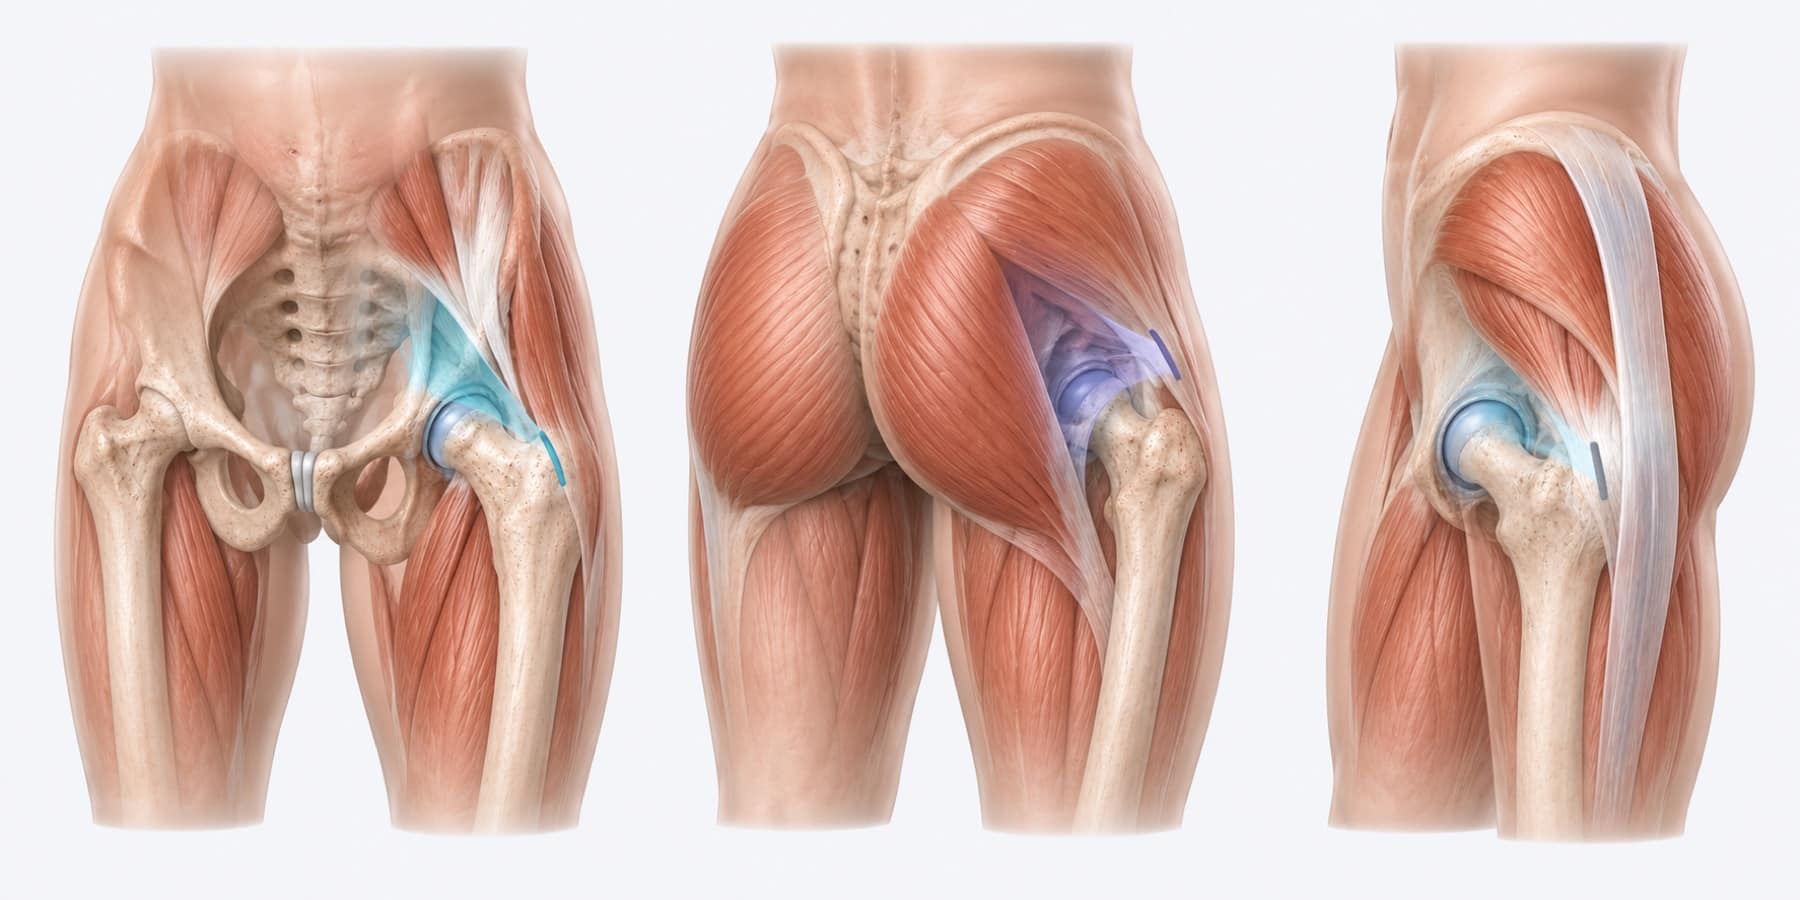
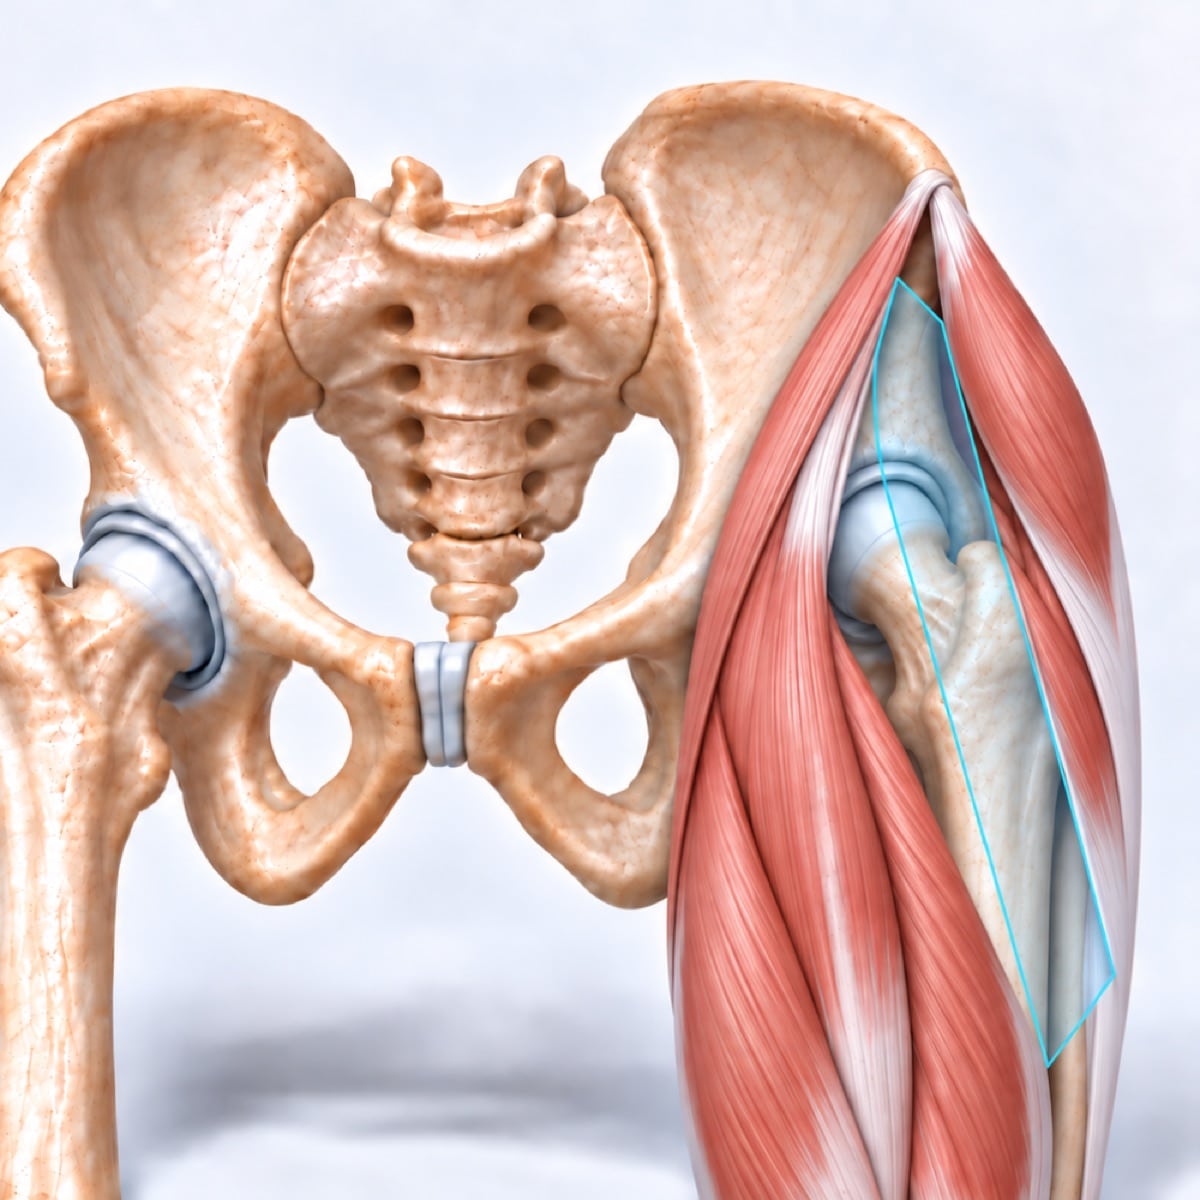 Anterior (front) |  Posterior (back) |  Lateral (side) | |
|---|---|---|---|
| Position on the table | On your back | On your side | On your side or back |
| Muscles | None cut off the bone | Buttock muscle split, small muscles lifted and repaired | Part of the muscle that levels your pelvis is lifted off the bone |
| First weeks | Less pain, walks better 1,2 | A little slower in the first weeks 1,2 | Slowest to get the side muscles back 5 |
| At six months and beyond | The same 1,2 | The same 1,2 | The same hip score 5 |
| Hip popping out (dislocation) | Fewest redo operations for dislocation in the Australian registry 4 | Highest of the three, though still uncommon 3,5 | Low 5 |
| Can the bursa be removed and the side tendons repaired at the same time? | No | Yes | Yes |
| Can the surgeon do a redo operation through it? | Yes, in experienced hands; Dr Yas does most of his redos from the front | Yes, and it gives the most room for the biggest reconstructions | Some |
| Risk that is special to it | Numb patch on the outside of the thigh 6; occasionally, tendon pain at the front of the hip 7 | Slightly more dislocation 3,5 | A limp from a weak side muscle 5; extra bone forming in the muscle 5 |
| Does Dr Yas use it? | Yes, for most hips | Yes, when it suits the hip | No |
What I tell every patient before an anterior hip
“I’d rather you heard the downsides from me before surgery than found them out afterwards.”— Dr Yas Edirisinghe
Common
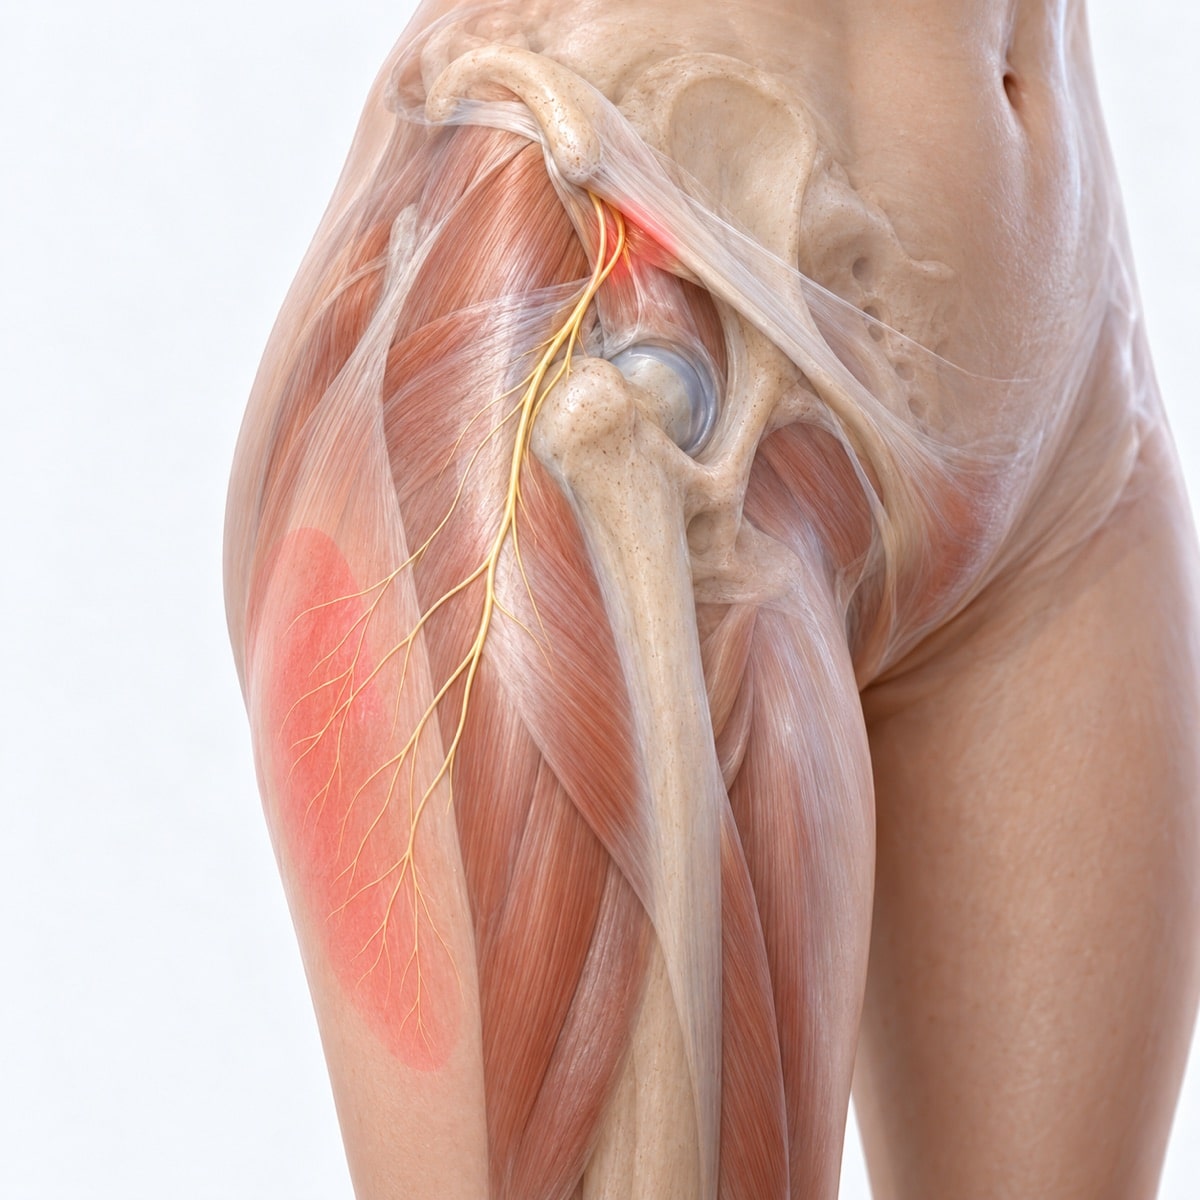
The numb patch. This one is common. A skin nerve runs across the front of the hip, right where the cut goes. In studies that asked patients about it, about one in three noticed a numb or tingly patch on the outside of the thigh afterwards. In most people it fades over the first year or two. In some it never fully goes, but it does not affect how the hip works. 6
Uncommon
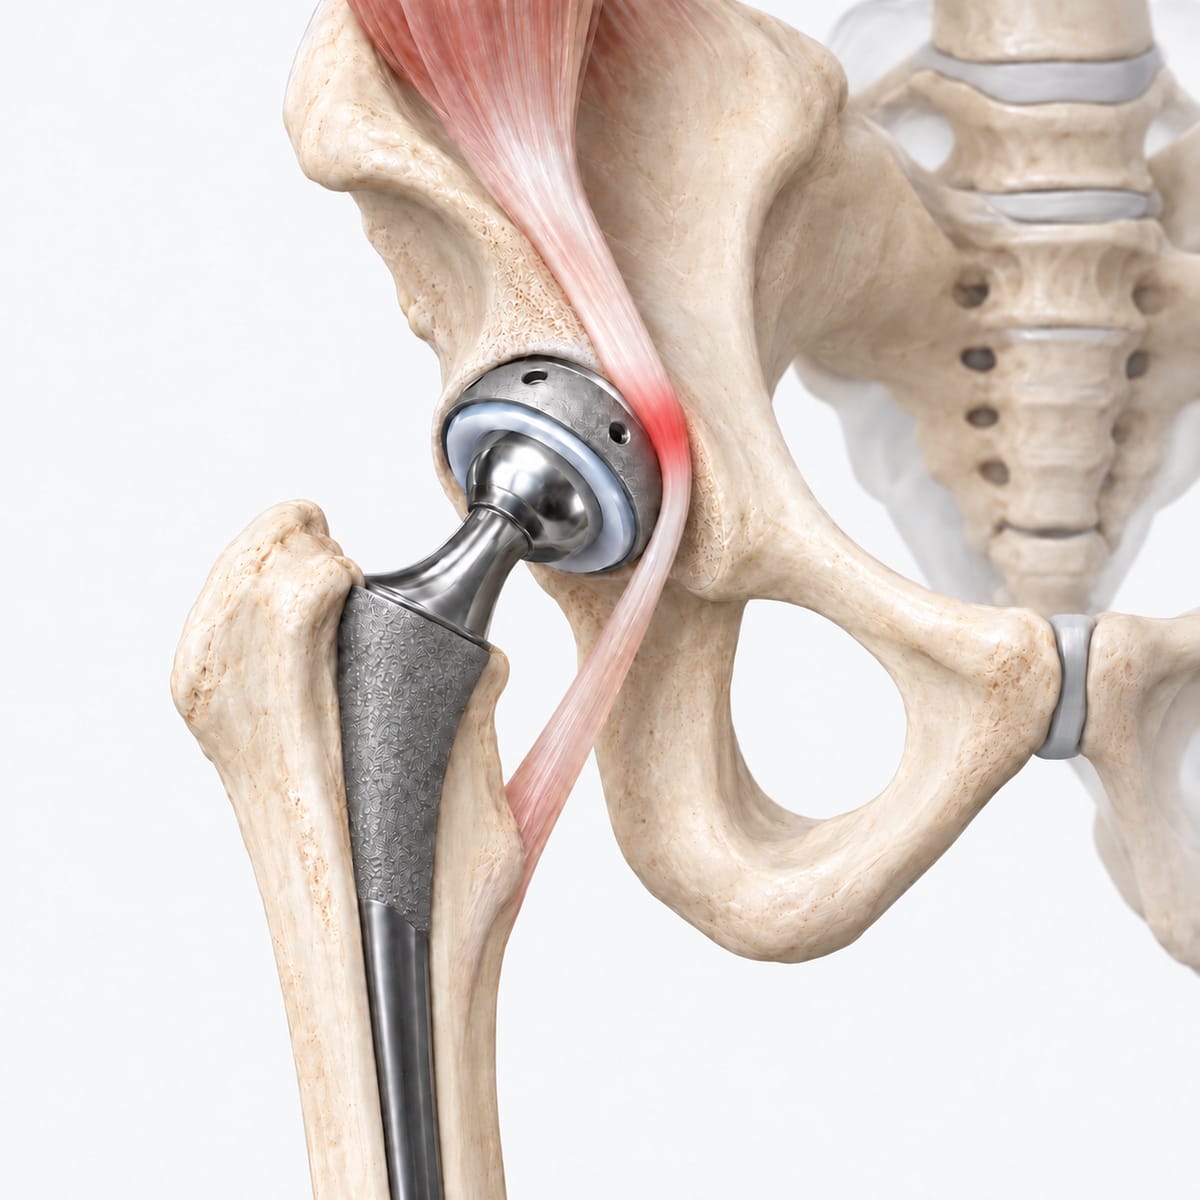
Tendon pain at the front. This one is uncommon. A big tendon (the psoas) runs over the front of the socket. Occasionally, if the edge of the new socket sits proud, the tendon rubs on it and causes groin pain. In one series of 559 anterior hips, about six in a hundred had this. 7 Most settle with an injection. A few need a small keyhole operation to release the tendon. 7
A limit
It cannot reach the side of your hip. If your bursa or gluteal tendons are the problem as well as your joint, the anterior approach cannot fix them. A posterior or side approach can.
Needs planning
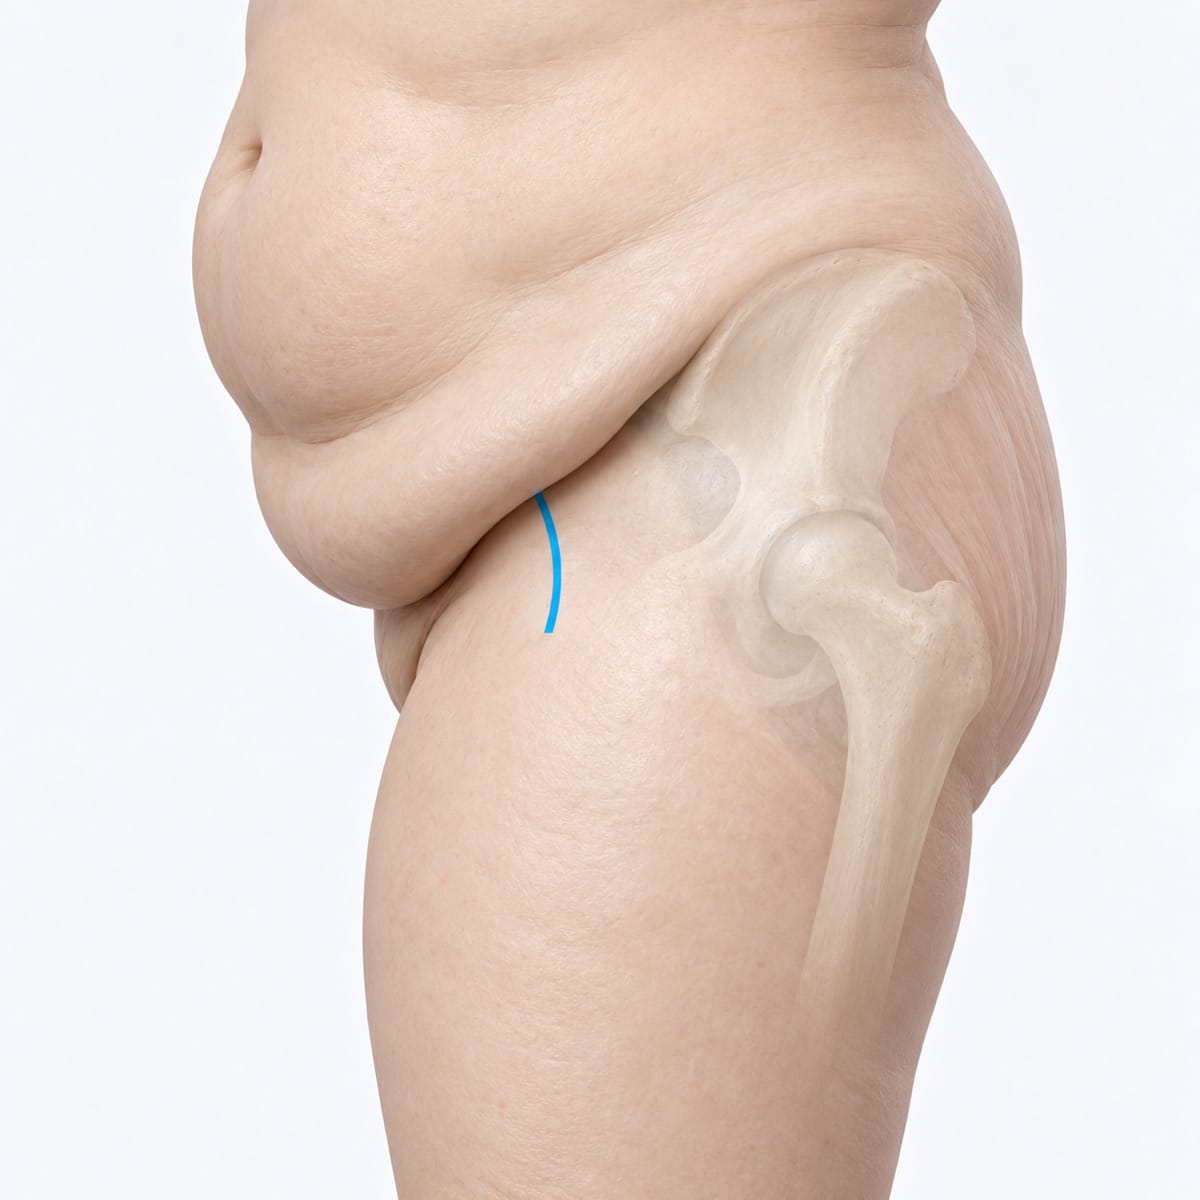
A heavier body shape needs planning. A deep skin fold at the front puts the wound under the fold, so the skin is prepared and the wound protected with that in mind. 8,9 The table below says more.
About the studies that worried people
Over the years there have been many studies and a lot of registry data on anterior hip replacement, and some of it showed worse results: more redo operations in the first year or two. Most of that comes down to the learning curve. The anterior approach is harder to learn than the posterior approach, because the surgeon works through a small window at the front. The Australian joint registry studied this directly. It found that a surgeon’s first 15 anterior hips were redone three times as often as their hips after 100, and that it took about 50 operations before the redo rate settled. 11 A Dutch registry study of 15,875 anterior hips put the learning curve at about 100 cases. 12 Registry figures include every surgeon at every stage of that curve.
That is why it is worth choosing a surgeon like Dr Yas, who does anterior hip replacements every week.
What is true of the posterior hip
- It is not “the old way”. It is the most common hip replacement in the world, and the approach most surgeons learn first.
- It hurts a bit more in the first week, and you may feel weaker pushing off up stairs for the first few weeks. The muscles that were split and repaired take time to settle. By six months, there is no difference. 1
- It has a slightly higher chance of the hip popping out. In pooled studies, about 1.4 in 100 posterior hips dislocated, compared with fewer than one in 100 overall. 3 Modern implants, larger ball sizes and careful repair have brought this down.
- It gives the surgeon the most room. For the biggest reconstructions, a broken pelvis, or a hip where the bursa and side tendons need treating at the same time, the posterior approach lets the surgeon fix whatever is found. That is why Dr Yas keeps it in his hands.
"The right operation is the one that fits the person"
“It is not about what I am good at, what my habit is, or which approach I do exclusively. I can tell you that no one approach is right for every patient, every time. The majority of the hip replacements I do, including redo hip replacements, I do as anterior hip replacements. I believe it is a very good way to replace a hip. But there are many situations where I choose, and recommend, a posterior approach as well. An 80-year-old woman with a painful, stiff hip and pain on the side of it, whose gluteal tendon has worn through with age and who can’t sleep on that side, needs a very different operation from a 55-year-old man who is frustrated that he can’t walk the dog or swing through a golf shot because his hip is getting stiffer and more painful. I would never say I am exclusive to one approach, because I think that is the wrong line to draw. The best approach is the one that suits you.“— Dr Yas Edirisinghe
Which approach suits which hip?
This is the table Dr Yas works through with every patient. It is a guide, not a rule.
| Your hip | Anterior (front) | Posterior (back) | What Dr Yas usually does |
|---|---|---|---|
| A typical worn hip: groin pain and stiffness, no surgery before | Good choice | Good choice | Anterior |
| Heavier build with a deep skin fold at the front | The wound sits under the fold. In published series, heavier patients had more wound problems after anterior hips: about 12 in 100 with a BMI over 30, against 2 in 100 below. 9 With skin preparation and wound precautions, it can still be the right choice. | Avoids the fold | Decided case by case |
| Heavier build, large buttock, flat front | A shorter path to the hip. In Dr Yas’s experience this may be an advantage, with the right skin preparation and precautions. | The way in is deeper | Decided case by case; often anterior |
| Pain on the side of the hip as well as the groin (bursitis, or worn gluteal tendons) | Cannot reach the bursa or the tendons | The bursa can be removed and the tendon repaired in the same operation | Posterior, so both problems are fixed in one operation |
| Previous hip surgery, or metalwork in the thigh bone | Possible in experienced hands | Full access | Decided case by case |
| A very stiff, deformed, or shallow hip (dysplasia) | Harder to get the stem in | More room to work | Decided case by case |
| A redo (revision) operation | Yes, for most redos in Dr Yas’s hands | Yes, for the biggest reconstructions | Anterior for most; posterior for the most extensive |
| Worried about the hip popping out | Fewest redo operations for dislocation in the registry 4 | Slightly higher 3 | Anterior, if the rest fits |
“No one approach is right for every patient, every time. The approach is chosen for your hip.”— Dr Yas Edirisinghe
Read more:
Food for thought: if you already have a posterior hip
Thousands of people in Adelaide have a posterior hip replacement and are reading about anterior hips for the first time. Here is the honest answer.
At six months and at one year, people with anterior and posterior hips feel the same.
That is the finding of an umbrella review that pooled 11 meta-analyses of randomised trials. 1
The anterior approach gets people moving a little sooner. That is real, and it is worth having. But it is a head start, not a better finish. If your posterior hip is working well, it is as good a hip as anyone’s.
If it is not working well, the approach is rarely the reason. The usual reasons are listed on the painful hip replacement page, and they are checked one by one. My hip replacement still hurts
Dr Yas's 4-step hip plan
1. Find the pain.
Joint, tendons and bursa, or both. Examination, X-ray, and a scan if the side of the hip is involved.
2. Plan in 3D.
Your hip is planned on a 3D model built from your own scan. Dr Yas positions the implants himself in the planning software. A model of your hip and a guide made for it are 3D-printed for use in theatre.
3. Choose the way in.
Anterior for most. Posterior when it will give you a better result. You will know which, and why, before the day.
4. Deliver and check.
The implant goes in to the plan. With an anterior hip, an X-ray in theatre checks the position before the wound is closed.
Planned on your hip, not an average one
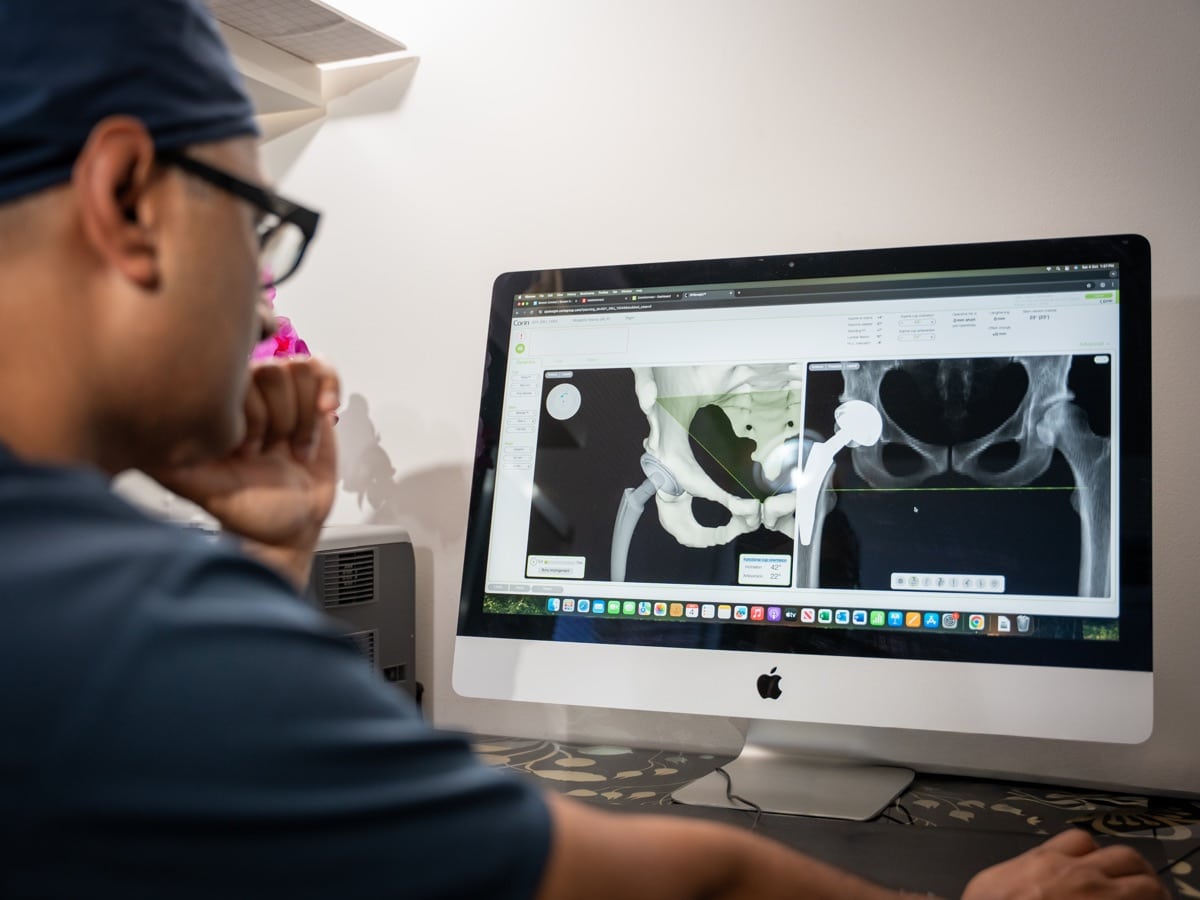
Before surgery you have a CT scan. From it, a 3D model of your pelvis and thigh bone is built on a computer. Dr Yas does the planning himself. He chooses the size of the socket and the stem, sets exactly where each will sit, and matches your leg length to the other side. He then moves the model through its range of motion on the screen, to check that the new ball will not catch on the socket rim or the bone.
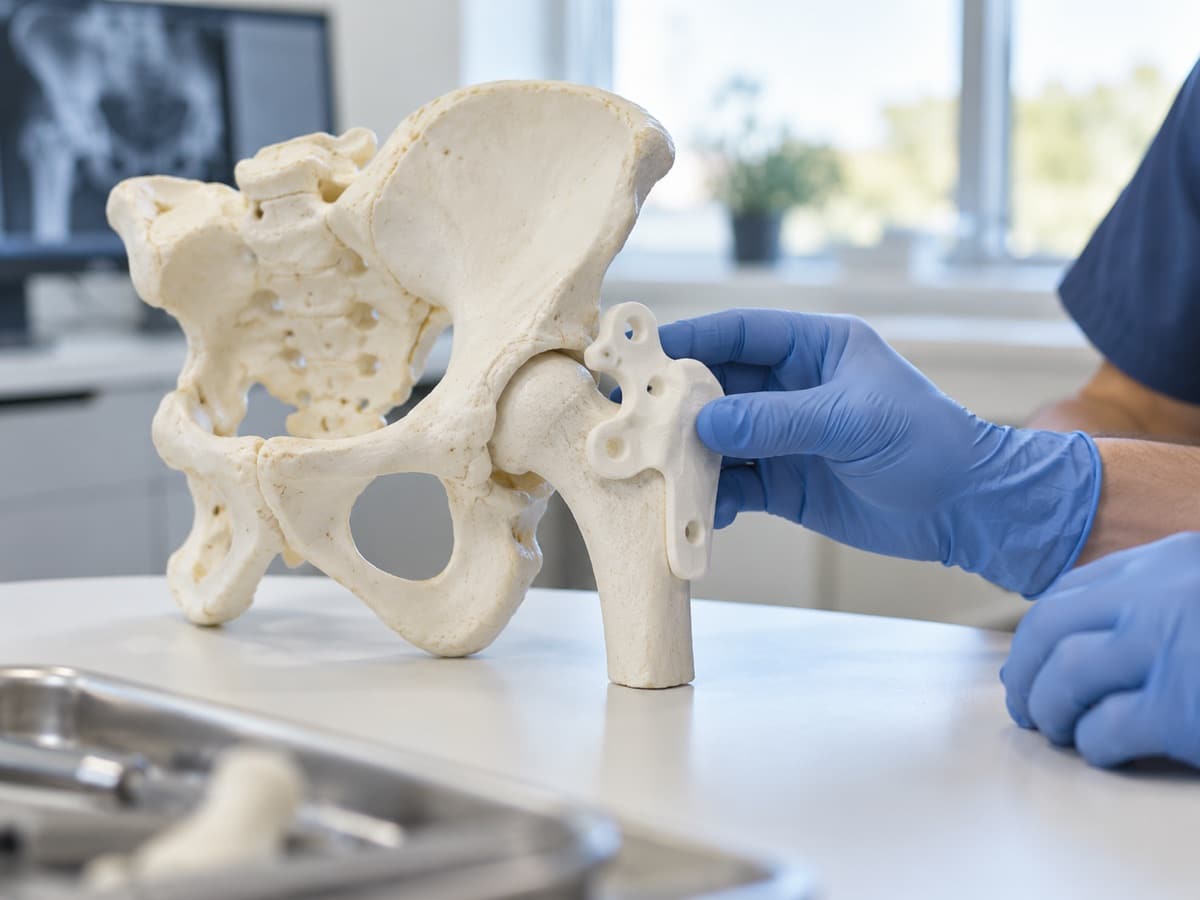
Two things are then 3D-printed from that plan: a model of your hip, and a guide shaped to fit your bone. In theatre, the guide shows Dr Yas where the plan says the implant should go. With an anterior hip, an X-ray confirms the position before the wound is closed.
“The implant is picked and positioned for your hip before we start. In theatre, the job is to deliver that plan exactly.”— Dr Yas Edirisinghe
The implants

| Part | Made of | Why |
|---|---|---|
| Socket (cup) | Titanium shell, with a liner | Bone grows onto titanium |
| Liner | Highly cross-linked plastic, or ceramic | Low wear |
| Ball (head) | Ceramic | Smooth, hard, very low wear |
| Stem | Titanium (uncemented) or polished steel alloy (cemented) | Chosen for your bone quality and age |
What recovery looks like, week by week
Day 1.
Up and walking with a frame or sticks, usually the same day. Pain is controlled with local anaesthetic and tablets.
Days 1–3.
Home. Anterior hips tend to go home about half a day sooner than posterior hips. 1
Week 2.
Wound review. Stitches are under the skin and dissolve. Driving from two weeks, once you are off strong painkillers. With an anterior hip, a numb patch on the outside of the thigh is common at this stage. 6
Week 6.
Walking without aids for most. Back to most daily activities.
3 months.
Pain and walking scores for anterior and posterior hips are close by now. 2
6 months to 1 year.
No difference between approaches. 1 The hip keeps improving for a year.




What it costs you
There is no extra surgeon’s fee for an anterior approach. Dr Yas honours your current insurance arrangements, and you will have a written estimate before anything is booked. Fees & billing
Not sure which approach suits your hip? Ask.
Send Dr Yas a question about your hip. He reads every one. No records to send: if you come in, he obtains your X-rays and history himself.
Ask Dr Yas a question
He reads every one.
Frequently asked questions
What is an anterior approach hip replacement?
A hip replacement done through the front of the hip, going between the muscles rather than cutting them. The implants and the result are the same as any other hip replacement. The way in is different.
Is anterior hip replacement better?
I had a posterior hip replacement. Is that inferior?
No. At six months and a year, people with posterior hips do just as well. 1 If your hip is working, it is a good hip.
What is the difference between anterior and posterior hip replacement?
Anterior goes in at the front between the muscles; posterior goes in at the back through the buttock muscle. Anterior recovers a little faster early on and has fewer redo operations for dislocation in the Australian registry. Posterior gives the surgeon more room, can reach the bursa and tendons at the side of the hip, and has slightly more dislocations. 1,3,4
What are the advantages and disadvantages of anterior hip replacement?
Advantages: no muscle cut, quicker early recovery, fewer dislocation redo operations in the registry, X-ray check during surgery. Disadvantages: a numb patch on the thigh (common), tendon pain at the front of the hip (uncommon), a higher wound risk in heavier patients, and it cannot reach the side of the hip. 1,4,6,7,9
Who is the best anterior hip replacement surgeon in Adelaide?
There is no “best”. What you can look for is a surgeon who does anterior hips regularly, explains both approaches, tells you the risks of each, and can do whichever your hip needs. Ask which approach they would choose for your hip, and why.
Who should not have an anterior hip replacement?
People whose bursa or worn gluteal tendons need treating at the same time, some people with a very stiff or deformed hip, some with previous surgery or metalwork in the thigh bone, and some heavier patients with a deep skin fold at the front. For these hips Dr Yas may recommend the posterior approach. Most other hips, including most redo operations, he does from the front.
Can I have an anterior hip if I am a bigger person?
Often, yes. The wound sits under the skin fold at the front, and in published series heavier patients had more wound problems after anterior hips, 8,9 so the skin is prepared and the wound protected with that in mind. In Dr Yas’s experience the anterior approach may still be the better option for some heavier body shapes, because the path to the hip is shorter from the front than through a large buttock. He decides case by case. Hip or knee replacement with a higher body weight
Why is the outside of my thigh numb after an anterior hip replacement?
A skin nerve crosses the front of the hip where the cut is made. About one in three people notice numbness. Most of it fades over the first year or two. 6
I have a torn gluteal tendon. Did I injure it?
Usually not. These tendons wear thin with age and part of them gives way, like a rope fraying. It is a wear problem that comes with age, not an injury, and it is treated that way.
How long will it last?
Anterior and posterior hips are redone at the same overall rate in the Australian registry. 4 Modern hip replacements last 20 years or more for most people.
References
- Nassar et al. Direct anterior approach and posterior approach for total hip arthroplasty: a systematic umbrella review of meta-analyses of randomized controlled trials. Orthopedic Reviews 2025 (PMC12103296).
- Movva S, Koduru SK, Roop D, et al. Clinical and safety outcomes after direct anterior total hip arthroplasty compared with conventional approaches: a systematic review and meta-analysis. J Orthop Case Rep 2026 (7 studies, 4,685 patients).
- Koster LA, et al. Dislocation rates by surgical approach in total hip arthroplasty: meta-analysis of 11 prospective studies (2,025 patients). J Orthop Surg (Hong Kong) 2023.
- Hoskins W, et al. Direct anterior versus posterior approach for cemented-stem total hip arthroplasty: AOANJRR analysis of 60,739 procedures. HIP International 2024.
- Sun M, Wang Y, Wei X, et al. Gait and function after total hip arthroplasty: a systematic review and meta-analysis of the Hardinge versus posterolateral approaches. BMC Musculoskelet Disord 2026 (26 studies, 245,620 patients).
- Dahm F, et al. Lateral femoral cutaneous nerve injury after direct anterior approach total hip arthroplasty: a review. Orthop Traumatol Surg Res 2021;107(8):103089.
- Buller LT, et al. Anterior iliopsoas impingement after direct anterior approach total hip arthroplasty. J Arthroplasty 2021;36(5).
- Argyrou C, et al. Total hip arthroplasty through the direct anterior approach in morbidly obese patients. Bone Jt Open 2022.
- Revelt N, Sleiman A, Kurcz B, et al. Acute surgical site complications in direct anterior total hip arthroplasty: impact of local subcutaneous tissue depth and body mass index. Arthroplasty Today 2024 (280 hips).
- Greater trochanteric pain syndrome: a scoping review (2021), PMC8298339, reporting Segal NA et al. 2007 (community prevalence) and Long SS et al. 2013 (877 hips with lateral hip pain).
- de Steiger RN, Lorimer M, Solomon M. What is the learning curve for the anterior approach for total hip arthroplasty? Clin Orthop Relat Res 2015 (AOANJRR; 5,499 THAs, 68 surgeons).
- Peters RM, ten Have BLEF, Rykov K, et al. The learning curve of the direct anterior approach is 100 cases: an analysis based on 15,875 total hip arthroplasties in the Dutch Arthroplasty Register. Acta Orthop 2022.